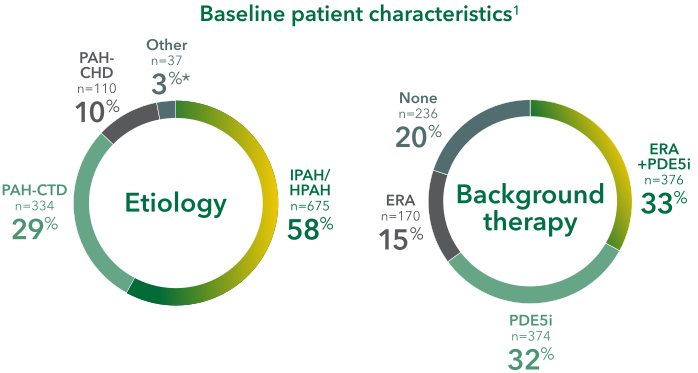
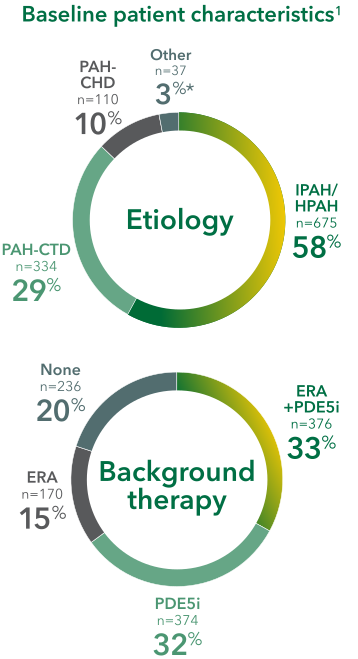
Uninterrupted treatment is key in managing pulmonary arterial hypertension (PAH, WHO Group I), a progressive disease.2
UPTRAVI IV Is for the Treatment of PAH (WHO Group I) in FC II-III Patients Who Are Temporarily Unable to Take Oral Therapy1
- Avoid treatment disruptions when your patients are unable to take oral therapy by temporarily transitioning them from their current oral dose to IV treatment and returning to UPTRAVI Tablets when possible1,3
Remain confident that your patients can receive UPTRAVI treatment at home, in the hospital, and after discharge
- Expected to maintain similar UPTRAVI efficacy and safety, with the exception of infusion-site reactions, when temporarily using UPTRAVI IV in the hospital1,3
- Bypass re-titration when transitioning between UPTRAVI IV and UPTRAVI Tablets1
- UPTRAVI Tablets (twice daily)*
- 200 mcg
- 400 mcg
- 600 mcg
- 800 mcg
- 1000 mcg
- 1200 mcg
- 1400 mcg
- 1600 mcg
- UPTRAVI IV (twice daily infusions)
- 225 mcg
- 450 mcg
- 675 mcg
- 900 mcg
- 1125 mcg
- 1350 mcg
- 1575 mcg
- 1800 mcg
Administer UPTRAVI IV twice daily by intravenous infusion at a dose that corresponds to the patient’s current dose of UPTRAVI Tablets.
Please see complete UPTRAVI IV dosing and administration instructions as listed in the full Prescribing Information.
Temporarily Switching to UPTRAVI IV From UPTRAVI Tablets Was Well Tolerated With Comparable Exposure to the Active Metabolite
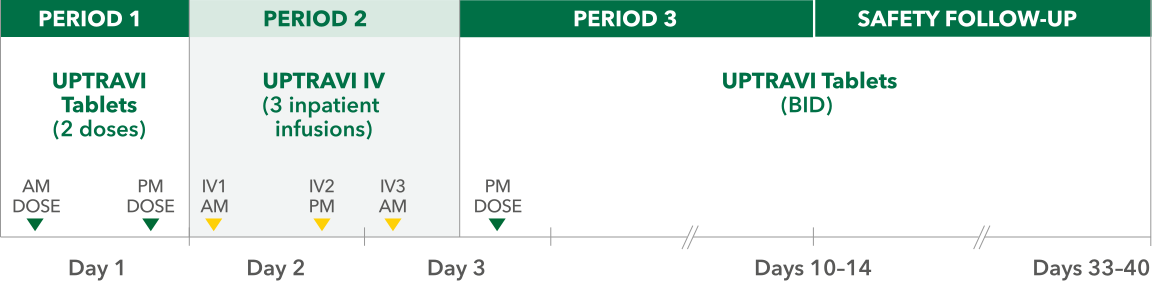
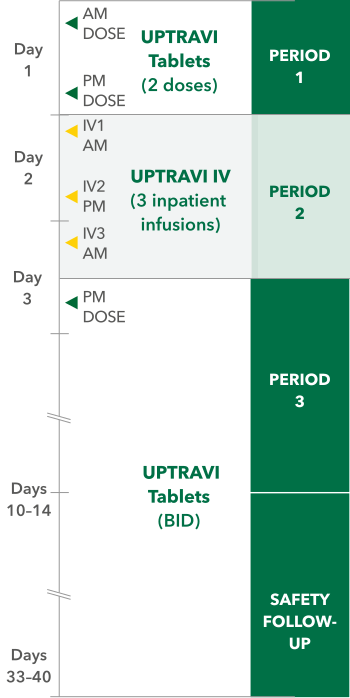
Study design3
- Phase 3, prospective, multicenter, open-label, single-sequence crossover study
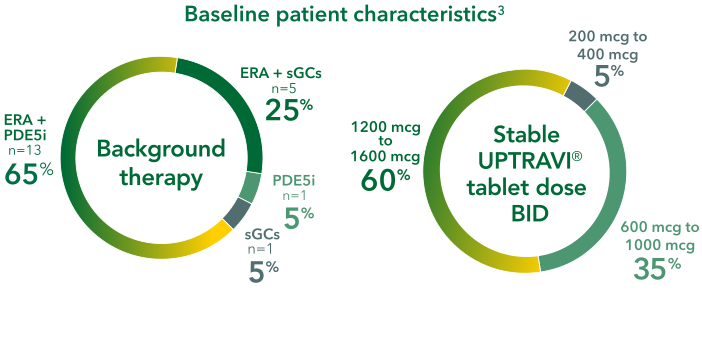
- Twenty patients with PAH in FC I-III† receiving a stable dose of UPTRAVI Tablets for ≥28 days prior to enrollment were included
- Patients were monitored to assess the safety, tolerability, and pharmacokinetics (including exposure to the active metabolite ACT-333679) of switching from a stable dose of UPTRAVI Tablets to a corresponding dose of UPTRAVI IV and back to UPTRAVI Tablets
- The dosing regimen for UPTRAVI IV was selected to help patients achieve similar exposure to the active metabolite when compared with UPTRAVI Tablets
20 Patients
Mean age: 57 years Female: 80%
65% FC II, 30% FC III
65% FC II, 30% FC III
Etiology
- Idiopathic or heritable PAH (70%)
- PAH-CTD (20%)
- PAH-CHD (5%)
- PoPH (5%)
Results1,3
Comparable exposure to the active metabolite following UPTRAVI Tablets and UPTRAVI IV administration
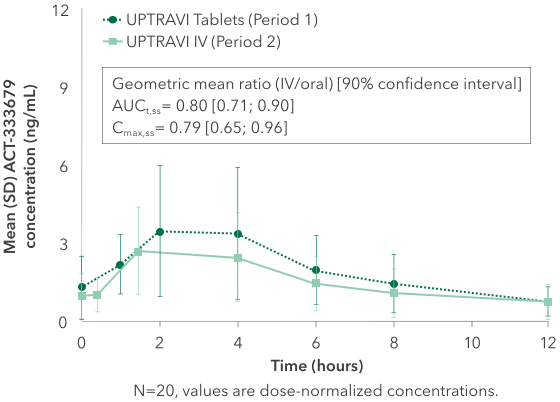
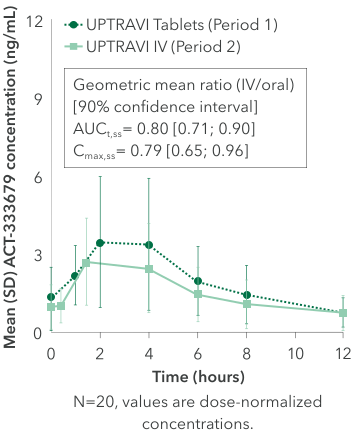
Time to the maximum concentration of the active metabolite was comparable
Safety1,3
- The transition from UPTRAVI Tablets to UPTRAVI IV and back was well tolerated: Patient tolerability was similar between UPTRAVI IV and Tablets
- 10% of patients reported infusion-site reactions during UPTRAVI IV administration, including infusion-site erythema/redness, pain, and swelling